How to write an MNT note that gets paid
MNT documentation guide for RDs who bill insurance: ADIME or SOAP, PES, time and units, medical necessity, signatures, and what payers check.
 By Javier Alvarez · 7 min read
An MNT note gets paid when it proves three things: the patient needed medical nutrition therapy, you delivered it, and the time you billed matches what actually happened.
Everything else, including the format (ADIME or SOAP), your software, and the length, is up to you. This guide covers what a paid note must contain, how to handle time and units, medical necessity wording, signatures and late entries, and what payers check during records requests.
This guide is for dietitians in private practice who bill insurance. It's not legal advice, and payer rules vary. When a rule is payer-specific, we say so and point to the source.
The paid-note checklist
A reviewer should be able to answer these questions without calling you.
The visit
- Date of service, and whether the visit was in person or telehealth (for telehealth: video or audio-only, and where the patient was located)
- Start and stop times, or total face-to-face minutes
- Your name and credentials as the rendering RD
- Name of the referring provider, if the payer requires a referral (Medicare MNT always does)
Why MNT was needed
- The medical diagnosis that justifies MNT, matching the ICD-10 codes on the claim
- Supporting data with a date and source: labs, anthropometrics, relevant medications
- For follow-up visits, what has changed since the last visit and why more visits are needed
What you did
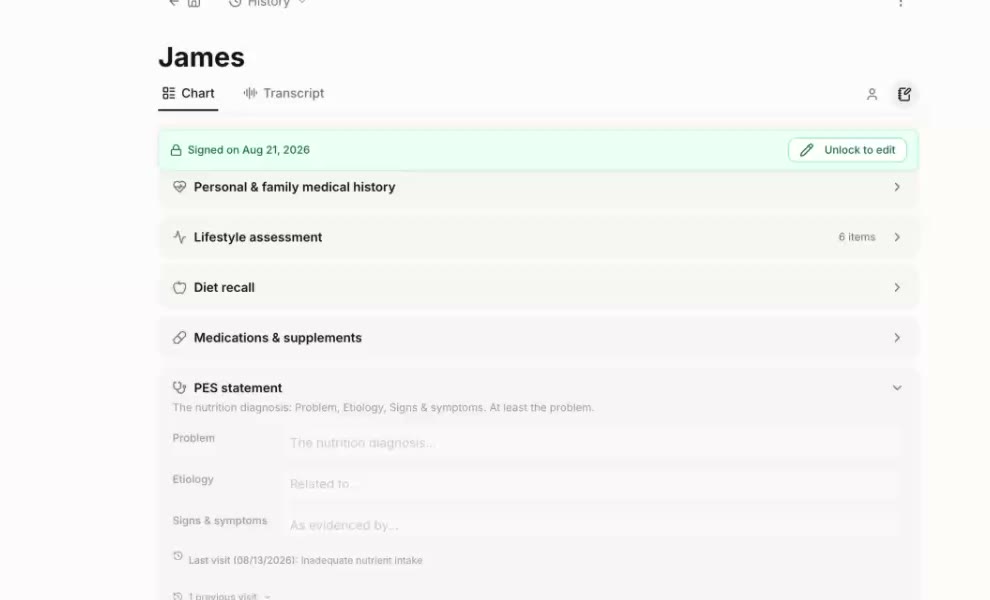
- Nutrition assessment and a nutrition diagnosis (PES statement)
- The intervention you delivered during this visit
- Measurable goals you set with the patient
What happens next
- What you'll monitor, progress on earlier goals, and when the next visit is scheduled
- Any coordination with the referring provider
Authentication
- Your signature, credentials and date on every note
If your note covers all of these points, the format matters far less. For complete examples, see the ADIME note example (includes a template plus initial and follow-up visits) and the SOAP note templates.
Format: ADIME or SOAP
Payers accept both. Your choice depends on who reads your notes most often.
ADIME (Assessment, Diagnosis, Intervention, Monitoring & Evaluation) follows the Academy's Nutrition Care Process. The nutrition diagnosis gets its own section, so medical necessity stands out clearly.
SOAP (Subjective, Objective, Assessment, Plan) is how physicians document. If most of your referrals come from doctors, SOAP notes align with what they expect to see.
Pick one format and stick with it. Switching between visits makes a chart harder to follow and hides how your patient is progressing. Compare the two approaches with the same visit written both ways in ADIME vs. SOAP notes.
PES statements: the bridge between diet and diagnosis
The PES statement (Problem related to Etiology as evidenced by Signs/symptoms) explains why this patient needs MNT, not just general nutrition advice. A strong PES:
- Identifies one nutrition problem that your intervention can change
- Names an etiology that your intervention will actually address
- Cites specific evidence from this visit's assessment: lab numbers, dates, weight changes, intake findings
A good PES also links to the medical diagnosis on the claim. A PES about fiber intake paired with an E78 hyperlipidemia code makes sense. The same PES next to a lone Z71.3 counseling code leaves the reviewer without a connection. See 25 PES examples by condition and use the free PES statement builder. For official terminology, use the Academy's freely available NCP terms or eNCPT, not informal labels that circulate online.
Time, units and start/stop times
97802 and 97803 are timed codes in 15-minute units, and 97804 (group) is in 30-minute units. The units on your claim must match the time documented in the note. This mismatch is the most common error reviewers find, and also the easiest to prevent.
| Face-to-face minutes | Units of 97802 / 97803 |
|---|---|
| 0 to 7 | 0 (not billable as a timed unit) |
| 8 to 22 | 1 |
| 23 to 37 | 2 |
| 38 to 52 | 3 |
| 53 to 67 | 4 |
| 68 to 82 | 5 |
The table uses the midpoint convention (a unit counts once you pass the halfway point). Most payers apply this to MNT, though some commercial plans set their own rules or per-visit caps. Full details and edge cases are in the 8-minute rule for dietitians, and the units calculator does the math.
To document time correctly:
- Write down real times. "10:02 to 11:04" is evidence. "60 min" typed after every visit looks like a default setting.
- Count only face-to-face time with the patient. Time spent on intake forms the patient filled out alone, charting after the visit, or messages between visits isn't part of the timed service.
- Bill what happened. A 52-minute visit is 3 units. Don't round the note up to 53.
- Use the right code for the visit. 97802 is the initial assessment and 97803 covers follow-ups and reassessments. Medicare says 97802 is used "only once for the initial assessment of a new patient" (Pub. 100-04, Ch. 4 §300.4). See 97802 vs. 97803 and the code pages for 97802 and 97803.
Duo Practice writes the ADIME or PES note from the recorded session, with the visit time and units filled in for you to review. Try Duo Practice free
Medical necessity: explain why, not just what
Medical necessity means the note shows that this visit was reasonable and needed for this patient's condition. Medicare applies this strictly to MNT. Coverage is limited to diabetes and renal disease with a physician referral. A Medicare MNT claim without one of these diagnoses will be denied as not reasonable and necessary (Ch. 4 §300.5; NCD 180.1). Commercial plans write their own policies and many list covered diagnoses by code.
Wording that supports medical necessity:
| What to show | Example |
|---|---|
| Specific findings | "A1c 8.4% (03/2026, per PCP)" instead of "A1c elevated." |
| The link to the condition | "Excess carbohydrate at dinner, contributing to post-dinner readings of 220 to 260 mg/dL." |
| Progress and what's left | "Beverage goal met; dinner pattern unchanged; continue MNT to address dinner carbohydrate." |
| A plan with an end point | The goals you'll measure and when you'll reassess. |
Wording that weakens your case: "discussed healthy eating," "patient doing well, continue plan," and assessment text copied unchanged from the previous visit. More examples and how to keep your documentation consistent across visits are in charting for medical necessity.
Signatures, AI scribes and late entries
Sign every note. Medicare reviewers look for "signed and dated medical documentation," and CMS may deny claims when entries lack required signatures (MLN905364). Use your electronic signature with your credentials. Don't leave notes unsigned as drafts.
AI scribes work if you sign them. CMS guidance states: "If you use a scribe, including artificial intelligence technology, sign the entry to authenticate the documents and the care you provided." You don't need to note who or what transcribed the entry. Your signature is what matters, so review an AI draft as carefully as if you had typed it yourself. Check the times, codes, the patient's own words, and anything the model filled in. The AI charting guide walks through how to review a generated note.
Late entries and corrections are permitted if labeled. CMS expects notes to be documented when services occur. When you need to amend, correct or enter a note late, "the date and author of any amendment, correction or delayed entry should be identifiable," and the change should be "clearly and permanently denoted" (Program Integrity Manual, Ch. 3 §3.3.2.5). In practice:
- Add an addendum dated today. Keep the original note unchanged.
- State what you're adding and why ("Late entry: start/stop times not recorded in original note; times from scheduling system").
- Never add information after a records request that wasn't true or known at the visit. That turns a documentation gap into a much bigger problem.
If you forgot to sign a note, CMS accepts a signed attestation from you for most medical documentation (not for orders).
Records requests: what payers check
Eventually a payer will request your notes, whether before payment or years later. What they verify is consistent: whether the patient was eligible, whether a referral existed if required, whether the diagnosis supports the code, whether time supports the units, whether the note demonstrates necessity, and whether it's signed. How this varies by payer (Medicare, Medicare Advantage, commercial plans) is explained in payer documentation requirements. When a request comes, follow your payer requested your chart notes: what to send, what to withhold, and the deadlines.
Payment now doesn't prevent the payer from recouping money later. The full strategy for documenting to withstand a post-payment review is in how to audit-proof your nutrition claims. If a claim is already denied for lack of necessity, see the CO-50 denial and how to appeal a denied nutrition claim.
Templates and tools
- ADIME note example & template: copy-paste template with a billing header, plus two invented visits.
- SOAP note templates: the SOAP version.
- PES statement builder and 25 PES examples.
- MNT units calculator: minutes to units for 97802/97803/97804.
- Nutrition intake form template: collects the history your assessment needs before the first visit.
- Recording consent rules by state: read this before you record visits for note-writing.
Sources
- Academy of Nutrition and Dietetics: Nutrition Care Process
- NCD 180.1: Medical Nutrition Therapy
- CMS Medicare Claims Processing Manual, Ch. 4 §300 (MNT)
- CMS Medicare Program Integrity Manual, Ch. 3 §3.3.2.4 to 3.3.2.5 (signatures, amendments, delayed entries)
- CMS MLN905364: Complying with Medicare Signature Requirements (July 2025)
- NCPro: Freely available NCP terms
Sources checked . Payer rules change; verify the member's benefits.
Frequently asked questions
Do insurance companies require ADIME or SOAP format?
No. Payers don't require a specific format. They check whether your documentation supports the claim. ADIME fits the Nutrition Care Process and SOAP aligns with how physicians document. Pick one, build a template, and use it consistently.
Can I use an AI scribe for MNT notes?
Yes, as long as you review and sign the note. CMS guidance states that if you use a scribe, including AI technology, you sign the entry to authenticate the documentation and care. Once you sign, it's your note. Verify the times, codes and findings match what actually happened.
Part of MNT documentation.